
Point-of-care imaging · Perspective
Why can a patient leave a clinic with a “normal” X-ray and still have no answer? A perspective on what point-of-care soft-tissue imaging could change about the next clinical decision.
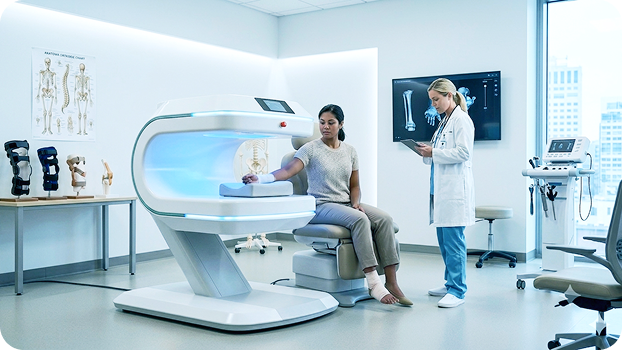
Here is the clinical question I keep coming back to: why can a patient leave a clinic with a “normal” X-ray and still have no answer? X-ray sees bone extremely well, but many common orthopaedic and sports injuries involve ligaments, tendons, muscles, cartilage and other soft tissues.
I believe those patients should not always have to leave, schedule another test, and return days later before the next decision can be made. The demand for a more direct path is already visible in orthopaedic practices, urgent-care clinics, sports organizations and field-care settings.
The gap after the X-ray
When a patient arrives with an injury, a clinician can examine the joint and obtain an X-ray quickly. If there is an obvious fracture, the path may be clear. But when the X-ray is negative and pain or loss of function continues, the most important question may still be unanswered.
Is the problem a ligament, tendon, cartilage, muscle or stress injury? Does the patient need immobilization, rehabilitation, specialist review, or simply time and reassurance? Today, getting more information can mean authorization, scheduling, a separate imaging-center visit, and another clinical encounter.
“We can usually get X-rays. But if it’s something soft tissue, we really don’t get good imaging.”
Dr David Helfet, Chief Emeritus of Orthopaedic Trauma Service, Hospital for Special Surgery
For a patient in pain, that gap can be the difference between leaving with a plan and leaving with another appointment.
The demand is a workflow problem, not only an imaging problem
Point-of-care demand is not about replacing every X-ray or every conventional MRI system. X-ray remains an essential first-line tool for bone, and hospital MRI will continue to serve complex imaging needs. The opportunity is to add a more informative next step when the clinical question centers on soft tissue.
The American Academy of Orthopaedic Surgeons has noted that sending a patient elsewhere for imaging can require more than one visit and separate the image from the treating physician’s immediate assessment. That is why I see access as the core issue: the information is valuable, but it is not always where the patient and clinician are making the decision.
A different path: exam, image, decision
We are developing Agile as a compact point-of-care system for 3D soft-tissue imaging in places such as orthopaedic clinics and sports medicine facilities. Our current design goals include operation in a standard room without a shielded suite or dedicated build-out, a push-button workflow for existing clinical staff, and a focused extremity scan of approximately 15 minutes.
That workflow remains a development objective and would depend on clinical validation and regulatory clearance. But it describes the change we are working toward: keeping useful soft-tissue information closer to the patient, the treating clinician, and the moment when the next step is chosen.
Better access could change when clinicians choose to image
When advanced imaging is expensive or difficult to schedule, it tends to be reserved for cases where the need is already substantial. If focused soft-tissue imaging becomes easier to access, clinicians could potentially investigate an injury earlier, monitor recovery more objectively, and make better-informed return-to-work or return-to-sport decisions.
Dr Michael Terry describes this possibility as a shift from reactive to proactive care. I find that framing powerful because it expands the value of access beyond speed. The question is not only how quickly we can see an injury; it is whether better access can change the course of care.
X-ray transformed medicine not only because of its physics, but because it became available where decisions were made. Our mission is to help give soft-tissue information that same point-of-care reach. Bone is only part of the picture. Soft-tissue injuries deserve to be seen.
See what same-visit imaging looks like in your clinic
Clinical pilots and partnerships — we reply within two business days.
Investigational device. Agile is under development and has not been cleared or approved by the FDA or any regulatory authority. It is not available for sale and is limited to investigational use. Capabilities, specifications and economics shown are design goals and subject to change; clinical claims are not implied.